Column · @angelouwov910
Small Houses, Big Heart: The Psychological Benefits of Intimate Elderly Care
Business Name: BeeHive Homes of Albuquerque West
Address: 6000 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Albuquerque West
At BeeHive Homes of Albuquerque West, New Mexico, we provide exceptional assisted living in a warm, home-like environment. Residents enjoy private, spacious rooms with ADA-approved bathrooms, delicious home-cooked meals served three times daily, and the benefits of a small, close-knit community. Our compassionate staff offers personalized care and assistance with daily activities, always prioritizing dignity and well-being. With engaging activities that promote health and happiness, BeeHive Homes creates a place where residents truly feel at home. Schedule a tour today and experience the difference.
6000 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
The longer I work in senior care, the more persuaded I am that scale silently forms whatever. Not just staffing ratios and budgets, however how it feels to awaken in the morning, who notices when you appear a bit off, and whether anybody remembers how you like your tea.
Large assisted living buildings and nursing homes have their place. They offer medical coverage, activities, transportation, and a complacency that numerous households really require. Yet, when I consider the most serene and deeply human minutes I have actually seen in elderly care, they seldom happen in a 100‑bed facility. They occur in small homes, at kitchen tables, on shaded decks, in familiar armchairs that have moved along with their owner.
Intimate care settings are not magic, and they are not ideal. However they typically open emotional advantages that are challenging to recreate at scale. Comprehending those advantages helps households make more thoughtful choices, whether they are considering assisted living, respite care, or long‑term residential options.
What "small home" care truly means
People utilize different terms: residential care home, board‑and‑care, micro‑community, small group home. The regulations differ from state to state and country to country, however the basic concept is consistent. Instead of a big institutional structure with long hallways and a main dining hall, you have a home or home‑like setting where a small number of older adults live together.
Typical features include:
- A restricted variety of citizens, typically in between 4 and 12.
- Shared common areas that look like a routine home rather than a facility.
- Fewer layers of personnel hierarchy, so caregivers, locals, and families understand each other personally.
- More flexible everyday regimens that can adjust to private preferences.
In real practice, the psychological tone of a small home depends even more on management, personnel culture, and the physical environment than on any licensing classification. I have walked into 6‑bed homes that felt cold and transactional, and I have fulfilled groups in 80‑resident assisted living neighborhoods who managed to produce amazing heat in spite of the scale.
Still, when you shrink the environment and simplify the structure, specific psychological advantages become simpler to achieve.
The psychological landscape of late life
By the time a family starts seriously exploring senior care, a lot has actually already taken place. Health modifications, hospitalizations, slow losses of capacity, moves away from a long‑time area, the death of pals or a spouse. On top of that, significant choices need to be made about safety, financial resources, and long‑term planning.
Underneath the logistics, numerous psychological requirements keep appearing:
- To feel seen as an entire person, with a history that still matters.
- To maintain some control over daily life, even when assistance is needed.
- To experience stability and predictability, especially if memory is fragile.
- To feel connected to a couple of relied on people, not perpetually surrounded by strangers.
- To maintain dignity in extremely intimate scenarios, like bathing or toileting.
Any senior care setting that takes these needs seriously is currently ahead. Small homes simply have an easier time equating those concepts into day-to-day practice.
Why small environments relieve the worried system
Watch someone with moderate dementia walk into a busy lobby loaded with people, tvs, and continuous motion, then watch the very same person step into a peaceful living room with two citizens reading and a caregiver folding laundry. The difference in body language is obvious. Shoulders relax, scanning eyes settle, speech becomes more fluid.
Chronic overstimulation is a surprise stressor in lots of bigger assisted living or memory care communities. Echoing hallways, paging systems, several activities in overlapping areas, personnel modifications across shifts, unfamiliar float workers from other systems. Older adults, specifically those with cognitive modifications, typically lack the spare psychological bandwidth to filter all this. When that happens, we see it as "roaming," "resistance," or "behaviors," but underneath, it can be distress.
Small homes reduce this background noise. Less citizens, less personnel, fewer doors and corridors. The brain has less to track. Regimens end up being clear. This calmer standard lets other favorable feelings surface area: contentment, interest, humor, even mischief. I have actually seen citizens who were referred to as "tough" in one setting develop into mild, cooperative people in a quieter small home, without any medication changes.
This does not imply small homes are always quiet. There can be laughter at the table, visiting grandchildren, a repair individual operating in the yard. The distinction is that the scale stays human. The nervous system can map the environment and feel fairly safe.
Attachment and belonging: knowing "these are my individuals"
Attachment does not end in childhood. In late life, particularly after the loss of a partner or long-lasting friends, the need to belong to a small, stable group ends up being extremely strong. When you position someone in a large senior care community, they might communicate with lots of various staff throughout a week. Some communities manage this well by assigning constant caregivers to particular citizens, however turnover and scheduling complexity still get in the way.
In a small home, homeowners see the same faces day after day. The caregiver who helps with the morning shower is typically the one who makes breakfast and sits at the table. The house manager most likely knows which grandchild is applying to college and which relative lives out of state. Families find out the caretakers' birthdays and inquire about their kids by name.
This repeated, low‑key contact develops genuine accessory. I keep in mind a female with innovative dementia, not able to recall her child's name, who might still look at a particular caretaker and state, "You are my safe individual." That safety had been earned over numerous peaceful mornings: the right water temperature, the additional towel, the mild touch when she flinched.

When citizens feel they come from a steady "little world," their anxiety decreases. They are more happy to accept personal care, more open up to attempting activities, more forgiving of small pains. Belonging is one of the greatest emotional benefits of intimate elderly care, and it is really tough to fake.
Preserving identity through daily rituals
Loss of independence injures, however not just in useful ways. Numerous older adults feel their identity wear down with every skill they can no longer safely carry out. Driving, cooking, handling medications, gardening, working with tools. When all of this vanishes at the same time, the emotional impact is enormous.
Small homes are especially well suited to maintaining identity through small, significant roles. In a big building, staff are often under pressure to "get through the list" of tasks. It appears quicker to do whatever for the resident. In a small home, there is more space to let somebody do a bit of what they still can, even if it takes twice as long.
A retired instructor might "assist" a caregiver checked out the mail and decide what to keep. A previous mechanic might be the one who "checks" the batteries on the smoke alarms with a staff member. Someone who constantly baked can sit at the kitchen table and shape cookie dough while a caretaker manages the oven.
These are not pretend activities. They are continuity of self. They advise the resident, and everybody else, that the person in the recliner is more than their diagnoses. I have actually seen anxiety soften when individuals restore these small roles. They are no longer "a fall risk in Room 203," they are Mary who folds the napkins, George who feeds the feline, Lila who waters the plants.
Emotional safety for households, not simply residents
Families often bring a heavy mix of regret, grief, and fatigue by the time they think about moving a loved one into assisted living or another senior care setting. Specifically for adult kids who promised "I will never ever put you in a home," the choice seems like a personal failure, even when 24‑hour care is plainly needed.
Intimate settings can ease that emotional burden in several ways.
First, interaction tends to be more individual and direct. Rather of an online portal and a generic "care group" email, households typically have the cell phone number of the primary caregiver or home supervisor. When Dad has a rough night, someone can text, "He was uneasy, we attempted music, he settled after some tea. No need to fret, however wanted you to know." These details assure families that their loved one is not simply "managed" however cared about.
Second, visits seem like coming by a home instead of stepping into an organization. I have seen teens who feared checking out a grandparent in a traditional nursing home relax instantly in a small, home‑like environment. They can sit at the kitchen area counter, chat with a caregiver, and feel part of daily life. This protects intergenerational bonds, which is emotionally important for everyone.
Third, small homes can share the load more flexibly. A child who has actually been offering round‑the‑clock care might begin with periodic respite care stays, providing herself healing time while her parent gets used to the environment. Because the setting is small, the personnel quickly discover the person's regimens, which makes each subsequent stay smoother. In time, if an irreversible relocation becomes essential, it seems like a continuation rather than a rupture.
Families who feel emotionally safe are much better able to stay associated with a healthy, sustainable way. That benefits the resident, who keeps significant connections, and the personnel, who get collaborative partners instead of burned‑out, resentful relatives.
Staff experience and how it shapes care
You can not talk about emotional results without talking about staff. Frontline caregivers bring the impact of the physical, emotional, and ethical labor in elderly care. Their well‑being straight affects the atmosphere homeowners feel every day.
Large assisted living neighborhoods might use more formal profession courses, training programs, and benefits, but they can also feel administrative. Schedules are rigid, interactions are task‑driven, and private caregivers might not see the long‑term effect of their work.
In a small home, staff experience is various. Caregivers frequently:
- Form long‑term, family‑like relationships with citizens and their relatives.
- Have more autonomy to adjust routines to resident preferences.
- See the immediate psychological impact of their existence, for much better or worse.
- Take pride in the "entire home," not simply their assigned tasks.
This can be deeply satisfying. I have actually satisfied staff who remained in one small home for a decade, following residents through the final chapters of their lives with remarkable dedication. That continuity is rare in bigger systems.
There are trade‑offs, of course. Smaller operations might struggle to offer top‑tier pay and advantages. Burnout is still a risk, especially if staffing is tight or management is weak. In an extremely small team, one harmful personality can poison the environment quickly. Households ought to not assume that "small" automatically suggests "healthy," but when the culture is favorable, the psychological causal sequence is remarkable.

When a larger setting may be better
Intimate care is not always the best response. There are scenarios where a bigger assisted living or competent nursing environment fits better, mentally as well as medically.
Residents with highly intricate medical needs might require 24‑hour licensed nursing, on‑site treatment services, specialized clinics, or fast access to hospital transfers. Some small homes can collaborate this, however numerous are not equipped for high‑acuity care.
Extremely extroverted residents, or those who draw energy from a wide range of social contacts and structured activities, often prosper in a bigger neighborhood. They like several clubs, big occasions, and a more busy atmosphere. For them, a really small setting might feel restricting and even lonely.
Families who live far away may prefer a bigger provider with more robust administrative systems, clear escalation courses, and a business structure they can hold accountable. A small, family‑run home without strong governance can drift into bad practices if oversight is weak.
The key is healthy. Emotional benefits originate from positioning in between the person's character, needs, and the environment's strengths. There is no single "right" design for all older adults.
What to try to find in an emotionally healthy small home
When families tour senior care alternatives, the focus frequently falls on safety features, staffing ratios, and expense. These matter. However it is equally essential to evaluate the psychological environment. In a small home it can be simpler to read, since there are less moving parts.
Here are signs that a small home is emotionally healthy:
- Residents are taken part in normal life: someone reading, someone napping, perhaps somebody folding a towel, instead of everyone parked in front of a television.
- Staff talk to locals respectfully, utilizing names and mild tones, even when residents are confused or duplicating questions.
- Personal items and pictures are visible, and spaces feel customized, not staged for marketing.
- The house smells like regular living (food, laundry) rather than strong disinfectant or masking fragrances.
- You notification moments of authentic love: a hand squeeze, a shared joke, a caretaker who pauses to listen rather than hurrying past.
If possible, visit unannounced after the first official tour. The second visit typically exposes the "genuine" daily rhythm.
Questions to ask when considering intimate elderly care
Families sometimes feel overloaded and do not know how to penetrate beyond the pamphlet. Focused questions help appear the emotional truth behind the marketing language.
Useful questions to ask consist of:
- How long have most of your caregivers been here, and what do you do to keep good staff?
- Tell me about a resident who was challenging to care for initially and how your group was familiar with them.
- What takes place here on a normal day for someone like my mother or father, from waking up to bedtime?
- How do you involve households, especially if we can not visit often?
- Can you share a current circumstance where a resident was upset, and how personnel helped them feel safe again?
The content of the answer matters, but so does the method it is delivered. Are staff members stiff and rehearsed, or do they seem reflective and truthful? Do they speak about homeowners with affection or annoyance? Do they consist of the older adult in the conversation where possible, or talk over them?
Integrating small homes with the larger care continuum
Intimate care settings rarely run in isolation. Often, they become part of a wider sequence: home care, respite care stays, longer residential care, sometimes hospice. The emotional advantage grows when these transitions feel connected instead of fragmented.
Respite care can be specifically powerful. A caregiver who has actually been supporting a spouse with dementia in the house might utilize a small home for brief remain at very first. These breaks allow the caregiver to rest, deal with medical appointments, or merely recharge. Equally essential, the individual receiving care slowly becomes familiar with the environment and the staff.
Over time, as the disease advances, what began as occasional respite care can evolve into a full‑time move. Because the relationships and regimens are currently in place, the emotional shock is minimized. The resident is not entering an unidentified structure however going back to a location where "my pals are."
Coordinated medical care makes a distinction too. When small homes develop strong connections with local primary care providers, home health, and hospice teams, residents experience less jarring transitions in and out of medical facilities. Personnel can pick up subtle modifications early and team up with clinicians who currently understand the person's worths and history. That connection supports dignity at the end of life.
Practical restrictions: cost, guideline, and availability
It would be unethical to discuss psychological benefits without acknowledging the practical barriers. Small homes are not equally available, and they are not always inexpensive. In numerous areas, they run as private‑pay assisted living or board‑and‑care, which can put them out of reach for households relying entirely on public benefits.
Regulatory frameworks in some cases lag behind reality. Rules composed for bigger centers might not adjust well to small homes, or the licensing classification that fits a small home design may not enable higher care needs. Good companies work artistically within these restrictions, but they can just flex so far.
Families in some cases have to make tough compromises. I have actually sat at kitchen area tables with children who preferred a particular small home mentally but chose a larger setting due to the fact that it accepted a public payer source that the small home could not. In those minutes, the work moves to extracting as much intimacy and personalization as possible within the selected environment.
Advocating for policy that supports a larger range of small, community‑based senior care choices is not a quick fix, yet it remains crucial. The emotional advantages described here are not high-ends. They belong to humane care in late life, and they should not be scheduled only for those who can pay leading rates.
Bringing the "small home" state of mind into any setting
Even when a real small home is not an alternative, households and specialists can borrow from the small‑scale method to enhance the psychological experience in bigger assisted living or nursing environments.
Focus on connection. Demand constant caregivers when possible. Discover their names, share household stories, and treat them as partners. That relational glue helps everyone.
Personalize the area. Even in a standard room, pictures, a preferred blanket, a familiar light, or a valued wall hanging can create psychological anchors. These things tell personnel who the individual is, not simply what care they need.
Protect rituals. If your father constantly shaved after breakfast, advocate for keeping that order. If your mother hoped or listened to a certain piece of music before bed, share that with staff. Small routines offer psychological structure.
Slow down key moments. Bathing, dressing, and mealtimes are mentally packed. Motivate caregivers to prevent rushing through them. A few additional minutes of calm, unhurried existence typically avoid agitation later.
Above all, keep telling the individual's story. In care plan conferences, in corridor talks with staff, in notes you leave at the bedside. Small homes naturally take in these stories because the scale is intimate. In bigger settings, families in some cases need to work a bit harder to weave the story into the everyday fabric.
The peaceful power of intimacy
When you strip away marketing terms and care models, what older grownups and their families often wish for is simple: to feel at home, to be known, and to be cared for by individuals who treat them as people, not tasks on a schedule.
Small homes are not a universal option, however they are a brilliant demonstration that scale matters. A handful of residents around a table, a caregiver who notices a brand-new tremor, a family member who feels comfortable enough to cry in the kitchen area while someone makes coffee for them, not simply for the resident. These are the minutes that form the emotional memory of late life.
Whether you ultimately select an intimate residential home, a bigger assisted living albuquerque assisted living community, or a mix of respite care and in‑home assistance, keeping these emotional priorities in focus changes the questions you ask and the details you see. Buildings, staffing charts, and service menus are just the skeleton. The small, daily gestures of intimacy offer the heart.
BeeHive Homes of Albuquerque West provides assisted living care
BeeHive Homes of Albuquerque West provides memory care services
BeeHive Homes of Albuquerque West provides respite care services
BeeHive Homes of Albuquerque West offers support from professional caregivers
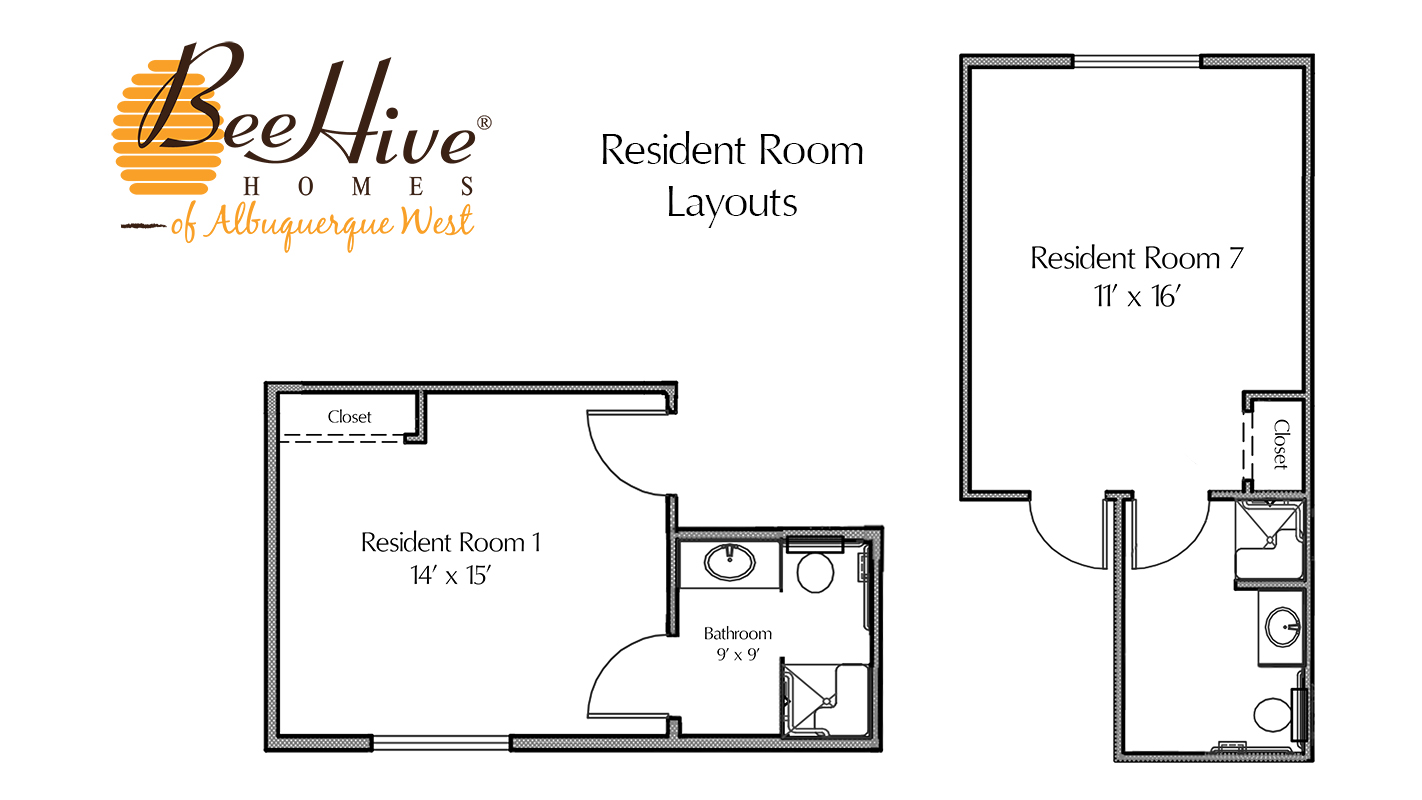
BeeHive Homes of Albuquerque West offers private bedrooms with private bathrooms
BeeHive Homes of Albuquerque West provides medication monitoring and documentation
BeeHive Homes of Albuquerque West serves dietitian-approved meals
BeeHive Homes of Albuquerque West provides housekeeping services
BeeHive Homes of Albuquerque West provides laundry services
BeeHive Homes of Albuquerque West offers community dining and social engagement activities
BeeHive Homes of Albuquerque West features life enrichment activities
BeeHive Homes of Albuquerque West supports personal care assistance during meals and daily routines
BeeHive Homes of Albuquerque West promotes frequent physical and mental exercise opportunities
BeeHive Homes of Albuquerque West provides a home-like residential environment
BeeHive Homes of Albuquerque West creates customized care plans as residents’ needs change
BeeHive Homes of Albuquerque West assesses individual resident care needs
BeeHive Homes of Albuquerque West accepts private pay and long-term care insurance
BeeHive Homes of Albuquerque West assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Albuquerque West encourages meaningful resident-to-staff relationships
BeeHive Homes of Albuquerque West delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Albuquerque West has a phone number of (505) 302-1919
BeeHive Homes of Albuquerque West has an address of 6000 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Albuquerque West has a website https://beehivehomes.com/locations/albuquerque-west/
BeeHive Homes of Albuquerque West has Google Maps listing https://maps.app.goo.gl/R1bEL8jYMtgheUH96
BeeHive Homes of Albuquerque West has Facebook page https://www.facebook.com/BeehiveABQW/
BeeHive Homes of Albuquerque West won Top Assisted Living Homes 2025
BeeHive Homes of Albuquerque West earned Best Customer Service Award 2024
BeeHive Homes of Albuquerque West placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Albuquerque West
What is BeeHive Homes of Albuquerque West monthly room rate?
Our base rate is $6,900 per month, but the rate each resident pays depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. We also charge a one-time community fee of $2,000.
Can residents stay in BeeHive Homes of Albuquerque West until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services.
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program.
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock.
Do we allow pets at Bee Hive?
Yes, we allow small pets as long as the resident is able to care for them. State regulations require that we have evidence of current immunizations for any required shots.
Do we have a pharmacy that fills prescriptions?
We do have a relationship with an excellent pharmacy that is able to deliver to us and packages most medications in punch-cards, which improves storage and safety. We can work with any pharmacy you choose but do highly recommend our institutional pharmacy partner.
Do we offer medication administration?
Our caregivers are trained in assisting with medication administration. They assist the residents in getting the right medications at the right times, and we store all medications securely. In some situations we can assist a diabetic resident to self-administer insulin injections. We also have the services of a pharmacist for regular medication reviews to ensure our residents are getting the most appropriate medications for their needs.
Where is BeeHive Homes of Albuquerque West located?
BeeHive Homes of Albuquerque West is conveniently located at 6000 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10am to 7pm
How can I contact BeeHive Homes of Albuquerque West?
You can contact BeeHive Homes of Albuquerque West by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/albuquerque-west, or connect on social media via Facebook
Residents may take a trip to the Petroglyph National Monument which offers scenic views and cultural significance that make it a meaningful outdoor destination for assisted living, memory care, senior care, elderly care, and respite care outings.